Thyroidectomy Recovery: Hypocalcemia Tingling, Recurrent Laryngeal Nerve Voice Changes & Calcium Taper
Surgeon-reviewed post-thyroidectomy protocol: recognizing parathyroid stun hypocalcemia (fingertip/lip numbness), vocal cord paresis, and calcium/calcitriol dosing.
Clinical Takeaway
Perioral numbness (tingling around the lips), fingertip paresthesias, and painful hand cramping after a total or partial thyroidectomy are classic signs of transient hypocalcemia caused by parathyroid gland devascularization or surgical stun. Prompt oral calcium carbonate and calcitriol supplementation prevents tetany and cardiac arrhythmias. Vocal hoarseness is usually temporary laryngeal edema, but sudden breathing distress or a rapidly expanding neck hematoma requires emergent airway decompression.
1. Parathyroid Stun & Postoperative Hypocalcemia
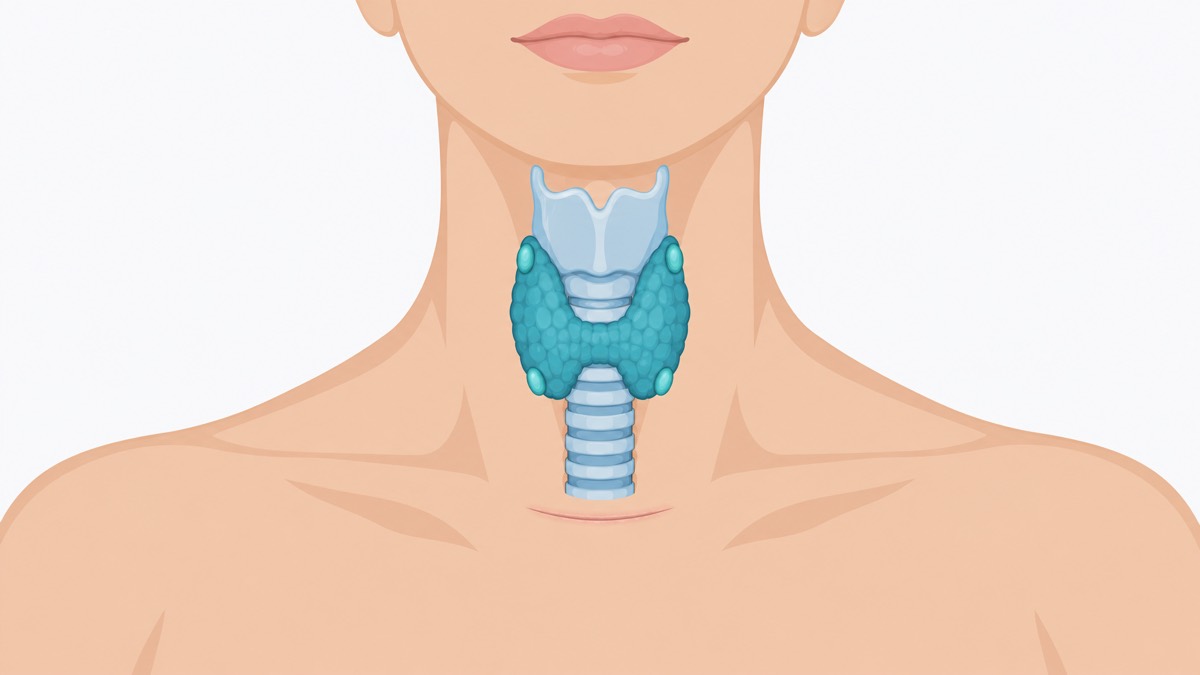
During a total or completion thyroidectomy, the surgeon meticulously dissects and preserves the four delicate parathyroid glands (superior and inferior pairs), each measuring no larger than a grain of rice. These glands receive an exquisite, fragile arterial supply primarily from branches of the inferior thyroid arteries.
Even with microscopic surgical precision, surgical manipulation, localized thermal energy from electrocautery, and transient venous congestion frequently induce 'parathyroid stun' (transient hypoparathyroidism). Without adequate parathyroid hormone (PTH) secretion, serum ionized calcium levels rapidly plunge within 12 to 72 hours post-operation[9].
2. The Chvostek & Trousseau Signs: At-Home Triage Tests
Low serum calcium (hypocalcemia) destabilizes cell membranes, causing neuromuscular hyper-excitability. Every patient must be familiar with the early, subtle sensory signs before muscle spasms develop:
Early Sensory Symptoms:
- Perioral Paresthesia: An electric, tingling, 'pins-and-needles' or vibrating sensation surrounding the lips and cheeks.
- Acroparesthesias: Tingling and numbness in the fingertips and toes.
- Metallic Taste: An unusual copper or metallic flavor on the tongue.
The 2 Classical Clinical Signs You Can Test at Home:
| Clinical Sign | How It Is Elicited | Positive Response & Meaning |
|---|---|---|
| Chvostek's Sign | Gently tap your index fingertip over the facial nerve, approximately 2 cm anterior to the earlobe and just below the zygomatic arch. | Involuntary twitching or spasm of the facial muscles on the same side, especially the corner of the lip and nose. Indicates neuromuscular irritability. |
| Trousseau's Sign (Main d'Accoucheur) | Inflate a home blood pressure cuff on your upper arm to 20 mmHg above your systolic pressure and hold for 2 to 3 minutes. | Carpal Spasm: Involuntary flexion of the wrist, thumb adduction, and extension of the fingers ('obstetrician's hand'). Highly specific for severe hypocalcemia. |
3. Oral Calcium & Calcitriol Taper Protocol
To prevent symptomatic hypocalcemia, our surgical protocol initiates prophylactic oral calcium carbonate (such as Tums ULTRA 1000 or Caltrate) combined with activated vitamin D (calcitriol / Rocaltrol):
The Standard Rescue Dosing Regimen:
- Routine Prophylaxis (Days 1 to 14): Calcium carbonate 1,000 mg to 1,500 mg elemental calcium orally three times daily with meals, plus calcitriol 0.25 mcg to 0.5 mcg twice daily.
- Acute Breakthrough Rescue Dose: If perioral tingling or fingertip numbness begins, immediately chew two 1,000 mg calcium carbonate tablets (such as Tums) with 8 ounces of water. Rest quietly for 30 minutes. If symptoms do not resolve within 45 minutes, chew two additional tablets and call your surgical on-call team.
- Weaning Phase: Parathyroid glands typically recover from stun within 2 to 6 weeks. Serum calcium and PTH are drawn at your 2-week follow-up before tapering calcitriol and calcium.
4. Recurrent Laryngeal Nerve Traction vs. Temporary Edema
Voice alterations after thyroid surgery are common and cause profound anxiety, particularly for professional voice users[2]. It is critical to differentiate between temporary mucosal edema and true vocal cord paresis:
- Intubation-Related Tracheitis & Edema (80% of Cases): The endotracheal tube sits directly between the vocal cords during surgery. This causes a raspy, husky voice, throat dryness, and mild fatigue when speaking loudly. It typically resolves within 7 to 14 days with vocal rest and steam inhalation.
- Recurrent Laryngeal Nerve (RLN) Neuropraxia: The RLN travels in the tracheoesophageal groove directly beneath the thyroid lobes[10]. Traction or stretching during lobe mobilization causes temporary conduction block. Symptoms include a breathy, whispered voice, inability to project volume, and coughing or choking when swallowing thin liquids. In 98% of cases, full nerve recovery occurs within 3 to 6 months.
- Superior Laryngeal Nerve (EBSLN) Injury: Affects pitch modulation. Patients speak normally in conversational tones but cannot produce high-pitched singing notes or project their voice across a noisy room.
5. The Expanding Neck Hematoma: Airway Emergency Signs
A compressive cervical hematoma occurs in approximately 0.5% to 1.5% of thyroidectomies, typically within the first 6 to 24 hours post-operation. Because the deep cervical fascia is dense and unyielding, bleeding beneath the strap muscles rapidly compresses the trachea.
This is a critical surgical emergency. Call 911 immediately if you develop:
- A visible, rapidly swelling firm lump or 'tight collar' feeling in the anterior neck.
- Progressive difficulty breathing or stridor (a high-pitched wheezing sound during inhalation).
- Inability to swallow your own saliva.
- Feeling like the neck dressing is choking you.
6. Incision Care & Safe Cervical ROM Stretches
Patients instinctively hold their necks stiff and rigid after surgery, fearing they will 'rip open' the incision. This causes debilitating muscle tension headaches and trapezius spasms. The incision is closed with deep absorbable sutures and high-strength surgical skin adhesive (Dermabond) that can withstand normal neck movement.
Beginning on Postoperative Day 2, perform gentle cervical range-of-motion exercises three times daily:
- Chin Tucks: Gently pull your chin straight back toward your spine without looking down.
- Lateral Rotation: Slowly turn your head to look over your right shoulder, hold for 5 seconds, then repeat to the left.
- Gentle Extension: Look up toward the ceiling to a comfortable 30-degree angle to stretch the anterior neck tissues.
Frequently Asked Questions (FAQ)
When should I start taking my levothyroxine (Synthroid) after total thyroidectomy?
Levothyroxine hormone replacement begins on the morning of Postoperative Day 1. Take it on an empty stomach with a full glass of water, at least 60 minutes before breakfast. Crucially, separate levothyroxine from your calcium supplements by at least 4 hours, as calcium binds thyroid hormone and blocks gastrointestinal absorption.
Can I get my neck incision wet in the shower?
Most thyroidectomy incisions sealed with waterproof Dermabond skin glue can be briefly showered 24 to 48 hours post-op. Let water run gently over the area, but do not scrub, soak, or submerge in a bathtub for 2 weeks.
How long will the firm ridge or lump under my scar last?
A firm, hard ridge beneath the incision line (the 'healing ridge') is entirely normal collagen synthesis and tissue reorganization. It reaches maximum firmness at weeks 4 to 6 and gradually softens over 6 to 12 months with gentle scar massage.
Peer-Reviewed Surgical References
- Haugen BR, Alexander EK, Bible KC, et al. 2015 American Thyroid Association Management Guidelines for Adult Patients with Thyroid Nodules and Differentiated Thyroid Cancer: The American Thyroid Association Guidelines Task Force on Thyroid Nodules and Differentiated Thyroid Cancer. Thyroid. 2016;26(1):1-133. [PubMed PMID: 26462967].
- Chandrasekhar SS, Randolph GW, Seidman MD, et al. Clinical practice guideline: improving voice outcomes after thyroid surgery. Otolaryngol Head Neck Surg. 2013;148(6 Suppl):S1-37. [PubMed PMID: 23733893].
- Edafe O, Antakia R, Laskar N, et al. Systematic review and meta-analysis of predictors of post-thyroidectomy hypocalcaemia. Br J Surg. 2014;101(4):307-20. [PubMed PMID: 24402815].
- Patel KN, Yip L, Lubitz CC, et al. The American Association of Endocrine Surgeons Guidelines for the Definitive Surgical Management of Thyroid Disease in Adults. Ann Surg. 2020;271(3):e21-e93. [PubMed PMID: 32079830].
- Stack BC Jr, Bimston DN, Bodenner DL, et al. AMERICAN ASSOCIATION OF CLINICAL ENDOCRINOLOGISTS AND AMERICAN COLLEGE OF ENDOCRINOLOGY DISEASE STATE CLINICAL REVIEW: POSTOPERATIVE HYPOPARATHYROIDISM--DEFINITIONS AND MANAGEMENT. Endocr Pract. 2015;21(6):674-85. [PubMed PMID: 26135962].
- Shaha AR, Jaffe BM. Practical management of post-thyroidectomy hematoma. J Surg Oncol. 1994;57(4):235-8. [PubMed PMID: 7990478].
- Jeannon JP, Orabi AA, Bruch GA, et al. Diagnosis of recurrent laryngeal nerve palsy after thyroidectomy: a systematic review. Int J Clin Pract. 2009;63(4):624-9. [PubMed PMID: 19335706].
- Christou N, Mathonnet M. Complications after total thyroidectomy. J Visc Surg. 2013;150(4):249-56. [PubMed PMID: 23746996].
- Gkanis V, Papaconstantinou D, Lanitis S, et al. Effectiveness of perioperative calcium and vitamin D supplementation in preventing post-thyroidectomy hypocalcaemia: network meta-analysis of randomized trials. BJS Open. 2026;10(4). [PubMed PMID: 42397982].
- Randolph GW, Dralle H, International Intraoperative Monitoring Study Group, et al. Electrophysiologic recurrent laryngeal nerve monitoring during thyroid and parathyroid surgery: international standards guideline statement. Laryngoscope. 2011;121 Suppl 1:S1-16. [PubMed PMID: 21181860].
- Rosato L, Avenia N, Bernante P, et al. Complications of thyroid surgery: analysis of a multicentric study on 14,934 patients operated on in Italy over 5 years. World J Surg. 2004;28(3):271-6. [PubMed PMID: 14961204].