Surgical Scar Care: Hypertrophic vs. Keloid Prevention, Medical Silicone Sheets & Cross-Friction Massage
Board-certified surgical scar protocol: Medical-grade silicone gel sheeting, the critical 90-day remodeling window, scar massage techniques, and UV sunscreen protection.
Clinical Takeaway
How you treat your surgical incision between weeks 3 and 12 dictates the final cosmetic appearance of your scar for the rest of your life. Medical-grade silicone gel sheeting remains the international gold standard in evidence-based plastic and general surgery, clinically proven to reduce hypertrophic and keloid scar formation by up to 86% by hydrating the stratum corneum and downregulating TGF-beta fibrotic cytokine signaling.
1. The 3 Phases of Scar Biology: The Remodeling Window
A surgical scar is not static; it is an intensely active biological metabolic zone that evolves over 12 to 18 full months. Incisions heal across three sequential phases:
- Phase 1: Epithelial Closure (Days 0 to 14): Keratinocytes migrate to bridge the gap. By day 14, the incision holds only about 5% to 10% of its ultimate tensile strength.
- Phase 2: Proliferation & Matrix Deposition (Weeks 2 to 6): Fibroblasts churn out high volumes of type III collagen and glycosaminoglycans. The scar appears bright red, hyperemic, and raised.
- Phase 3: Maturation & Collagen Remodeling (Weeks 6 to 52): Type III collagen is systematically lysed by matrix metalloproteinases and replaced by organized, cross-linked bundles of high-tensile type I collagen. This is the critical window where proactive scar therapy determines whether your scar becomes a thin, flat silver line or a thick, painful ropy cord.
2. Hypertrophic Scars vs. True Keloids: Diagnostic Differences
Patients often label any red or raised scar as a 'keloid.' However, hypertrophic scars and true keloids are distinct clinical entities with radically different biological behaviors and treatments:[3]
| Diagnostic Feature | Hypertrophic Scar | True Keloid Scar |
|---|---|---|
| Anatomical Boundaries | Remains strictly confined within the original boundaries of the surgical incision. | Invades and expands into surrounding healthy dermis, like a benign fibrotic neoplasm. |
| Onset Timeline | Develops rapidly within 4 to 8 weeks after surgery; peaks at 6 months, then gradually regresses over 1–2 years. | Can appear months to years after surgery; does not regress spontaneously and continues to grow indefinitely. |
| Genetic & Anatomical Predilection | Occurs across all races; common in areas of high skin tension (shoulders, abdomen, joints). | Marked predilection for darker skin phototypes (Fitzpatrick IV–VI); common on earlobes, chest (sternum), and deltoids. |
| Response to Surgical Excision | Excellent response to surgical scar revision with tension-relieving closure. | Extremely high recurrence rate (50–100%) if excised alone without adjuvant radiation or triamcinolone. |
3. Silicone Gel Sheets: The Gold-Standard Evidence & Usage Guide
International clinical consensus guidelines for scar management universally recommend medical-grade silicone sheets or 100% silicone gel as the primary first-line prophylactic therapy for all surgical scars[2].
How Silicone Works:
Silicone does not work through chemical absorption. Instead, it creates a semi-occlusive microscopic barrier that reduces trans-epidermal water loss (TEWL) by up to 50%. This deep stratum corneum hydration signals epidermal keratinocytes to stop producing pro-fibrotic cytokines (specifically Transforming Growth Factor Beta-1 and Beta-2), instructing fibroblasts to downregulate excessive collagen production.
The 12-Hour Protocol:
- Wait until the surgical incision is 100% closed, dry, and all scabs have detached (typically 2 to 3 weeks post-surgery). Never apply silicone to open wounds!
- Clean the scar with gentle soap and water, then dry completely.
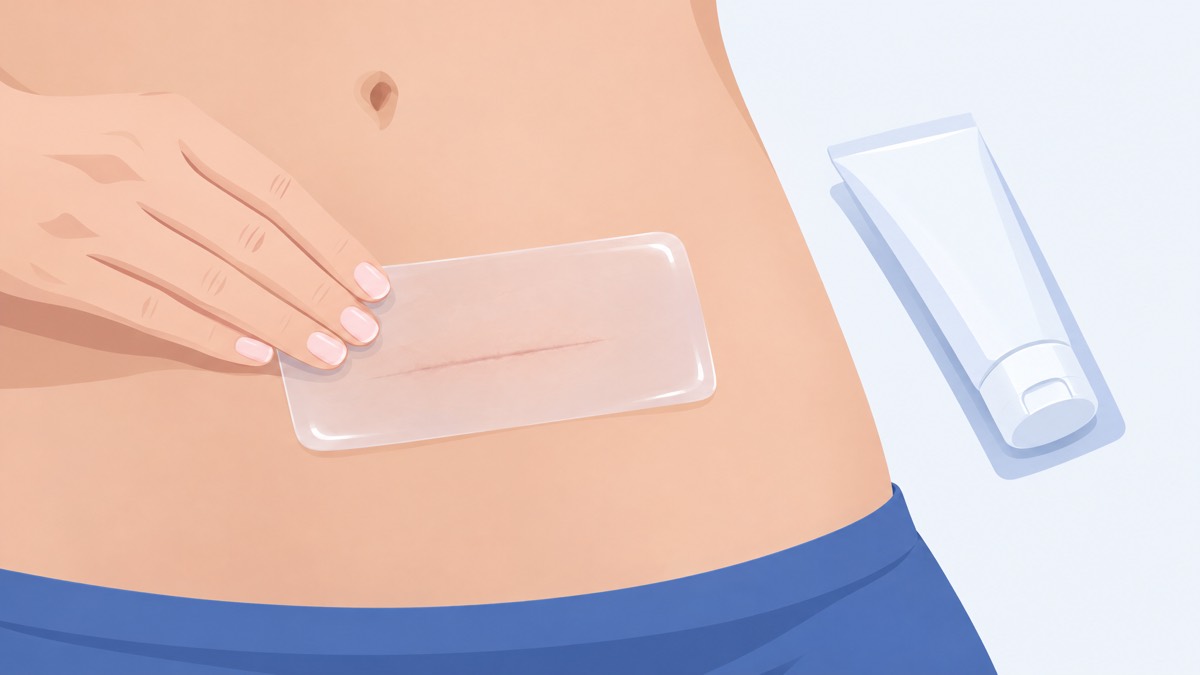
- Apply the medical-grade silicone sheet, ensuring it overlaps the scar margin by at least 1 cm in all directions.
- Wear for at least 12 to 24 hours daily for a minimum duration of 12 to 16 weeks. Wash the silicone sheet daily with mild soap and reuse until adhesive properties diminish.
4. Cross-Friction Scar Massage: Breaking Disorganized Collagen Fibers
Without mechanical guidance, collagen fibrils deposit in random, chaotic swirling patterns that bind the epidermis to underlying subcutaneous fat, muscle, or fascial layers (adhesions). Cross-friction scar massage breaks these tethering bands and forces collagen bundles to align parallel to skin stress lines.
The 3-Step Massage Method (Perform 5 minutes twice daily starting at Week 3):
- Step 1: Circular Friction: Using the pads of your index and middle fingers, apply firm, downward pressure directly on the scar line. Move your fingers in small, tight circles along the entire length of the incision.
- Step 2: Cross-Friction (Perpendicular): Apply pressure and move your fingers perpendicular across the scar back and forth. You should feel the scar tissue moving over the deeper tissues underneath.
- Step 3: Skin Rolling: Gently pinch the scar between your thumb and index fingers and lift it upward away from the underlying tissue, rolling it gently between your fingertips.
5. UV Photoprotection: Preventing Permanent Hyperpigmentation
Immature scar tissue contains an abundance of active melanocytes and immature vascularity. Ultraviolet (UV) radiation triggers profound post-inflammatory hyperpigmentation (PIH). Once UV light cooks melanin into remodeling dermal scar tissue, the dark purple or brown discoloration can become permanent.
Protect your scar with broad-spectrum mineral sunscreen (SPF 50+ containing zinc oxide or titanium dioxide) every single day for at least 12 to 18 months, even on overcast days. Physical sun-protective clothing or UPF 50+ tape provides superior protection compared to chemical lotions.
6. Clinical Interventions: Intralesional Steroids & Pulsed Dye Lasers
If a scar continues to thicken, itch intensely, or hurt despite 8 to 12 weeks of faithful silicone therapy, schedule a clinical consultation with your surgeon for second-line interventions:
- Intralesional Corticosteroids (Triamcinolone Acetonide): Direct micro-injections of triamcinolone (10–40 mg/mL) inhibit fibroblast proliferation, halt collagen synthesis, and relieve unbearable pruritus. Injections are spaced 4 to 6 weeks apart.
- Pulsed Dye Laser (PDL 595 nm): Selectively targets oxyhemoglobin in the microvasculature supplying the scar, collapsing excessive vessels and blanching erythema while inducing collagen remodeling.
- 5-Fluorouracil (5-FU) Blends: Combining low-dose 5-FU antimetabolite with triamcinolone prevents corticosteroid-induced skin atrophy and telangiectasias while achieving superior flattening of recalcitrant keloids.
Frequently Asked Questions (FAQ)
When is it safe to start putting scar cream or silicone on my incision?
You must wait until the wound is 100% epithelialized with zero scabbing, drainage, or open gaps—typically between Day 14 and Day 21 post-operation. Applying topical creams to unsealed incisions introduces bacteria and causes wound dehiscence.
Are onion extract creams (like Mederma) as effective as silicone gel?
No. Rigorous clinical head-to-head randomized trials have repeatedly demonstrated that topical onion extract is no more effective than simple petroleum jelly. Silicone sheeting remains the evidence-based gold standard backed by international consensus guidelines.
Why is my surgical scar so intensely itchy?
Postoperative scar pruritus is caused by regenerating cutaneous nerve endings firing spontaneously, alongside localized histamine and cytokine release during the proliferative healing phase. Applying cold compresses, hydrating with pure silicone gel, and gentle scar massage provide immediate relief.
Peer-Reviewed Surgical References
- Monstrey S, Middelkoop E, Vranckx JJ, et al. Updated scar management practical guidelines: non-invasive and invasive measures. J Plast Reconstr Aesthet Surg. 2014;67(8):1017-25. [PubMed PMID: 24888226].
- Gold MH, McGuire M, Mustoe TA, et al. Updated international clinical recommendations on scar management: part 2--algorithms for scar prevention and treatment. Dermatol Surg. 2014;40(8):825-31. [PubMed PMID: 25068544].
- Berman B, Maderal A, Raphael B. Keloids and Hypertrophic Scars: Pathophysiology, Classification, and Treatment. Dermatol Surg. 2017;43 Suppl 1:S3-S18. [PubMed PMID: 27347634].
- O'Brien L, Jones DJ. Silicone gel sheeting for preventing and treating hypertrophic and keloid scars. Cochrane Database Syst Rev. 2013;2013(9):CD003826. [PubMed PMID: 24030657].
- Mustoe TA, Cooter RD, Gold MH, et al. International clinical recommendations on scar management. Plast Reconstr Surg. 2002;110(2):560-71. [PubMed PMID: 12142678].
- Bleasdale B, Finnegan S, Murray K, et al. The Use of Silicone Adhesives for Scar Reduction. Adv Wound Care (New Rochelle). 2015;4(7):422-430. [PubMed PMID: 26155385].
- Robles DT, Berg D. Abnormal wound healing: keloids. Clin Dermatol. 2007;25(1):26-32. [PubMed PMID: 17276198].
- Son D, Harijan A. Overview of surgical scar prevention and management. J Korean Med Sci. 2014;29(6):751-7. [PubMed PMID: 24932073].
- Wasserman JB, Copeland M, Upp M, et al. Effect of soft tissue mobilization techniques on adhesion-related pain and function in the abdomen: A systematic review. J Bodyw Mov Ther. 2019;23(2):262-269. [PubMed PMID: 31103106].
- Ogawa R. Keloid and Hypertrophic Scars Are the Result of Chronic Inflammation in the Reticular Dermis. Int J Mol Sci. 2017;18(3). [PubMed PMID: 28287424].
- Gauglitz GG, Korting HC, Pavicic T, et al. Hypertrophic scarring and keloids: pathomechanisms and current and emerging treatment strategies. Mol Med. 2011;17(1-2):113-25. [PubMed PMID: 20927486].
- Ogawa R. Mechanobiology of scarring. Wound Repair Regen. 2011;19 Suppl 1:s2-9. [PubMed PMID: 21793962].